
Table of Contents
Why Is Nerve Pain Worse at Night? Causes, Biological Triggers, and Non-Surgical Relief
If you lie awake at night feeling burning, tingling, electric shocks, or an agonizing throbbing in your feet, legs, or arms, you are likely asking: why is nerve pain worse at night? During the busy daylight hours, neuropathic pain may feel manageable or fade into the background. However, the moment your head hits the pillow and the bedroom grows quiet, those sensations often flare up with surprising intensity.
In fast-paced metropolitan hubs like Hyderabad, thousands of individuals—ranging from corporate professionals dealing with desk-bound spine compression to patients managing diabetic peripheral neuropathy—struggle with nighttime pain flare-ups. This nocturnal surge is not imaginary, nor is it merely a mental trick caused by a quiet room. It is driven by specific physiological, hormonal, temperature, and neurological shifts that occur when your body prepares for rest.
Understanding the biological mechanisms behind nighttime pain escalation is the first step toward reclaiming your sleep. Modern interventional pain medicine provides targeted, non-surgical pain relief options that treat irritable nerves directly at their origin, helping you bypass the frustration of sleepless nights.
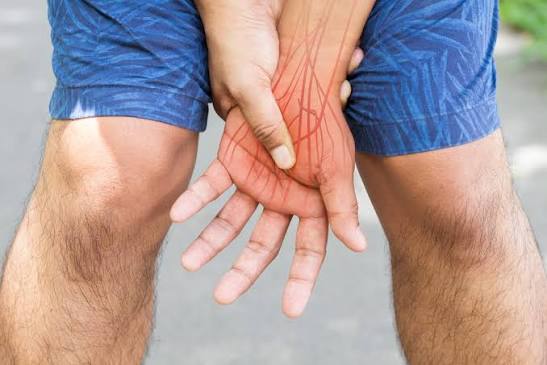
What Is Nocturnal Neuropathic Pain Flare?
Circadian and Neurological Changes in Nighttime Pain
Pain perception can change between daytime and nighttime. During the day, activity, environmental stimulation, and other competing sensory inputs may divert attention away from pain. At night, reduced stimulation and a quieter environment can make existing pain sensations feel more noticeable.
Daytime vs. Nighttime Pain Perception
| Daytime Balance | Nighttime Amplification |
|---|---|
| Higher daytime cortisol activity may influence inflammatory and stress responses. | Lower nighttime cortisol levels may coincide with changes in inflammatory and pain-regulatory processes. |
| Active brain and environmental stimulation can provide competing sensory input and distraction. | Dark and quiet surroundings can make burning, tingling, or stabbing sensations more noticeable. |
| Warmer peripheral tissues may feel more comfortable for some people. | Cooler extremities at night may alter sensory perception in some individuals. |
Understanding Why Nerve Pain Intensifies at Night
Nocturnal nerve pain escalation is a well-documented physiological phenomenon caused by a combination of circadian rhythm shifts, reduced anti-inflammatory cortisol levels, peripheral body temperature drops that heighten nerve sensitivity, and the absence of daytime sensory distractions, which allows the brain to focus entirely on abnormal pain signals.
According to research recognized by the International Association for the Study of Pain (IASP), neuropathic pain arises from damaged or hyper-excitable nerve fibers that fire spontaneous “ectopic” electrical signals. At night, multiple biological changes align to amplify these signals to the brain.
How Is Interventional Pain Management Different from Standard Care?
When dealing with severe nocturnal pain, many patients rely on temporary remedies that fail to address the underlying source of nerve irritation. Interventional pain medicine offers a targeted, medically sound middle ground.
Standard Conservative Care
Standard conservative management usually relies on oral pain medications, anti-seizure drugs (like gabapentin or pregabalin), muscle relaxants, and topical creams. While oral drugs can help reduce general nerve sensitivity, they circulate throughout the entire body and often cause systemic side effects like morning grogginess, brain fog, weight gain, or stomach distress. Furthermore, oral tablets do not fix physical issues like a herniated disc pinching a spinal nerve root or a compressed nerve channel.
Traditional Surgical Options
When conservative therapies fall short, patients are sometimes told that open spine surgery, bone fusion, or surgical nerve decompression are their only remaining choices. Open surgery involves structural alterations, hospital stays, long recovery periods, and inherent risks such as scar tissue formation (epidural fibrosis), which can sometimes irritate nerves further.
The Interventional Pain Specialty
An interventional pain doctor uses high-resolution diagnostic imaging (fluoroscopy or ultrasound) to identify the precise nerve segment transmitting abnormal pain signals. Using minimally invasive pinhole procedures, specialists apply targeted treatments—such as epidural steroid injections, selective nerve root blocks, pulsed radiofrequency, or radiofrequency ablation—directly to the affected nerve. This targeted approach calms hyper-excitable nerves at the source without open surgery or heavy reliance on systemic medications.
How Targeted Interventional Relief Works: A Step-by-Step Clinical Protocol
Addressing persistent nerve pain requires a clear, step-by-step diagnostic and therapeutic strategy to soothe irritated nerve roots and restore normal signal transmission.
1.Step 1: Diagnostic Mapping & High-Resolution Imaging:Pinpointing the precise nerve root or peripheral pathway causing pain.
A specialist performs a thorough neurological examination to map dermatomes (nerve pain paths). Advanced MRI scans or diagnostic ultrasound are evaluated to identify exact structural points of nerve compression, inflammation, or entrapment.
2.Step 2: Image-Guided Diagnostic Local Block:Confirming the exact generator of nocturnal pain signals.
Under real-time fluoroscopic or ultrasound guidance, a small amount of local anesthetic is placed precisely around the suspected nerve. If your pain drops significantly within minutes, the primary pain generator is confirmed.
3.Step 3: Gentle Local Anesthesia & Precise Access:Ensuring complete patient comfort in an outpatient setting.
On the day of the therapeutic procedure, local anesthesia is applied to thoroughly numb the skin and tissue pathway, keeping the experience virtually painless.
4.Step 4: Targeted Interventional Delivery (Injection, RFA, or Hydrodissection):Interrupting pain signals or calming local tissue inflammation.
Depending on the underlying cause, an anti-inflammatory agent, a targeted radiofrequency energy pulse, or fluid hydrodissection is delivered directly to the compressed nerve. This calms chemical inflammation, interrupts hyperactive pain signals, and separates surrounding scar tissue.
5.Step 5: Rehabilitation & Sleep Restoration:Resetting normal sleep cycles and facilitating active physical recovery.
With nocturnal pain signals quieted, normal sleep architecture can resume. Patients begin tailored physical therapy exercises to rebuild core stability and posture without triggering sharp nerve flares.
Primary Biological Causes Behind Worse Nerve Pain at Night
Several distinct physiological processes converge in the evening to make nerve pain feel more severe.
1. The Cortisol Drop and Inflammatory Surges
Cortisol is your body’s natural anti-inflammatory hormone. Its levels peak in the early morning to help you wake up and naturally decline in the evening. As anti-inflammatory cortisol drops, systemic inflammatory chemicals (cytokines) increase, allowing damaged or compressed nerves to become more inflamed and hyper-sensitive at night.
2. Loss of Daytime Sensory “Gating”
During the day, your brain receives millions of competing sensory inputs—visual stimuli, ambient sounds, movement, and work tasks. According to the Gate Control Theory of pain, these active signals help “close the gate” to pain transmission in the spinal cord. In a quiet, dark bedroom, competing inputs vanish, leaving your brain to focus almost entirely on abnormal nerve signals.
3. Temperature Drops and Peripheral Hypersensitivity
Core body temperature drops slightly at night to promote sleep, causing blood flow to shift inward and peripheral extremities (feet and hands) to cool down. In damaged peripheral nerves, cooler temperatures can trigger spontaneous firing of hypersensitive C-fibers, causing increased burning and tingling sensations in conditions like diabetic neuropathy or sciatica.
4. Postural Pressure and Mechanical Nerve Compression
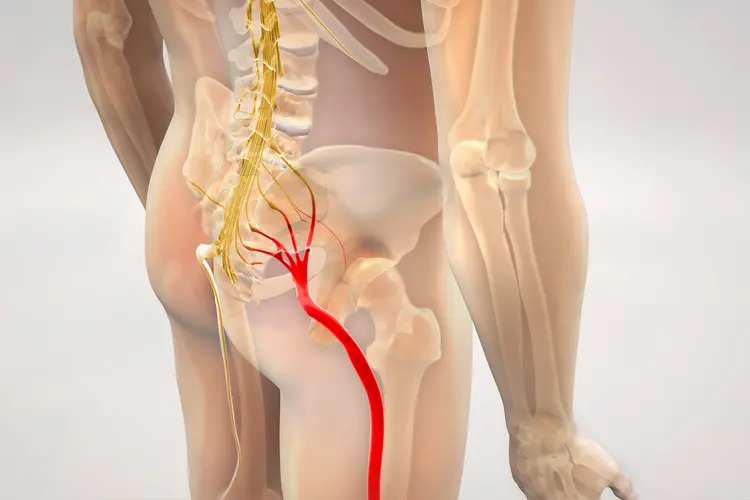
Lying still in bed for extended periods can apply continuous pressure to vulnerable nerves. For example, sleeping with a bent knee or knee position that strains the sciatic nerve, or lying on an unsupportive mattress that allows the lumbar spine to sag, can increase physical compression on pinched nerve roots.
Comparison of Treatment Approaches for Nighttime Nerve Pain
| Treatment Modality | Primary Mechanism | Clinical Benefits | Expected Results Timeline | Ideal Patient Profile |
| Oral Neuropathic Medications | Alters brain/spinal neurotransmitters to dull pain | Non-invasive; easily accessible | Requires weeks to titrate; may cause daytime drowsiness | Mild, generalized neuropathy without structural nerve pinching |
| Image-Guided Epidural / Nerve Block | Delivers targeted anti-inflammatory medicine to nerve roots | Calms localized inflammation directly at the spine or joint | Fast pain reduction within days; improves sleep quality | Pinched spinal nerves, sciatica, or herniated disc pain |
| Radiofrequency Ablation (RFA) | Uses thermal energy to interrupt nerve pain signals | Long-lasting relief without permanent surgical changes | Typically lasts 6 to 18 months; repeatable if needed | Chronic facet joint pain or severe localized nerve pain |
| Spine / Decompression Surgery | Physically cuts bone/tissue to widen nerve pathways | Direct mechanical decompression | Requires months of surgical healing and physical rehab | Severe motor weakness, bowel/bladder loss, or failed interventional care |
Who Is Suitable for Interventional Pain Treatments?
Understanding whether you are a good candidate for non-surgical interventional care helps you take control of your health journey.
You May Be a Candidate If:
- Burning, electric, or throbbing pain worsens at night and severely disrupts your sleep.
- You experience sciatica, herniated disc pain, canal stenosis, or diabetic peripheral nerve distress.
- Oral medications cause unwanted side effects like heavy morning grogginess, memory haze, or stomach irritation.
- Standard physical therapy is difficult to perform because pain flares up during movement or at rest.
- You want to avoid major spinal surgery or extended post-operative recovery periods.
What to Expect: Before, During, and After Treatment
Knowing what to expect before, during, and after an image-guided interventional procedure helps remove uncertainty and prepares you for a smooth recovery.
Before the Procedure
Your treatment plan begins with a detailed diagnostic assessment. Your specialist will perform a neurological exam, check your reflexes, map dermatomal pain patterns, and review MRI or CT imaging. You will receive clear pre-procedure guidelines, including simple advice on temporarily pausing blood-thinning medications if needed.
During the Procedure
- Outpatient Setting: Procedures are performed safely in a specialized day-care suite using local anesthesia.
- Precise Guidance: Real-time fluoroscopy (X-ray) or high-resolution ultrasound ensures exact needle placement near the affected nerve.
- Minimal Discomfort: The procedure typically takes only 15 to 30 minutes, with local numbing ensuring your comfort throughout.
After the Procedure
- Immediate Recovery: You rest comfortably in a recovery area for 30 to 45 minutes before heading home the same day.
- Progressive Relief: Pain signals usually begin to calm over the following few days, allowing for deeper, undisturbed sleep.
- Rehabilitation: Once nighttime pain calms down, tailored physical therapy can begin to strengthen surrounding muscles and prevent future nerve irritation.
When Should You Consider Seeing an Interventional Pain Specialist?
If you have been managing chronic pain for more than 6 weeks with limited relief from medication or physiotherapy, a consultation with a fellowship-trained interventional pain specialist is the logical next step. Dr. P. Purohithi at Apollo Hospital, Kondapur, Hyderabad, specialises in precisely diagnosing and treating the source of your pain using image-guided, minimally invasive techniques — without defaulting to surgery.
Holding prestigious international credentials, including FIPM (Fellowship in Interventional Pain Management) and IDRA, Dr. Purohithi offers expert care at Meraki Pain Management Center. By combining detailed clinical examinations with advanced image-guided diagnostics, Dr. Purohithi creates individualized treatment plans that calm hyperactive nerves, improve sleep, and help you return to an active, comfortable life.
Frequently Asked Questions
Why does nerve pain feel like burning or electric shocks?
Damaged or compressed nerves often lose their protective outer coating (myelin) and develop abnormal ion channels. This causes them to fire chaotic, spontaneous electrical pulses that the brain interprets as burning, stabbing, or electric shock sensations.
How do I know if I need a pain management specialist?
If nerve pain wakes you up at night, causes progressive numbness or weakness, or fails to improve after 4 to 6 weeks of conservative care, consulting a pain management specialist Hyderabad is recommended to identify the root cause and explore targeted treatments.
How long does radiofrequency ablation (RFA) last for nerve pain?
Radiofrequency ablation typically provides relief for 6 to 18 months, depending on nerve regeneration speed and individual physiology. The procedure can be safely repeated if pain eventually returns.
Is an epidural steroid injection for sciatica painful?
The procedure is performed under local anesthesia. While you may feel a mild sensation of pressure as medicine enters the epidural space near the affected nerve, sharp pain is carefully controlled throughout the brief procedure.
Can non-surgical pain relief help me avoid spine surgery?
Yes. Clinical studies show that image-guided interventional procedures—such as targeted epidural blocks, radiofrequency ablation, and nerve hydrodissection—can successfully resolve pain in over 80–85% of pinched nerve and sciatica cases, helping patients avoid surgery.
How much does a nerve block cost in Hyderabad?
The cost of an image-guided nerve block or interventional procedure depends on the specific nerve involved, the guidance technology used (ultrasound vs. fluoroscopy), and facility settings. A consultation at an established pain clinic Hyderabad provides a clear breakdown tailored to your care plan.
Can I consult Dr. P. Purohithi at Apollo Hospital Kondapur for nighttime nerve pain?
Yes. Dr. P. Purohithi evaluates complex neuropathic pain disorders and provides advanced, image-guided interventional treatments at Meraki Pain Management Center, located within Apollo Hospital, Kondapur, Hyderabad.

Reclaim Peaceful Nights and Restful Sleep
Understanding why is nerve pain worse at night helps replace anxiety with a clear plan for recovery. You do not have to accept sleepless nights, morning fatigue, or progressive nerve discomfort as an unshakeable part of your life.
If you are seeking an accurate diagnosis and modern, non-surgical treatment options in Hyderabad, Dr. P. Purohithi at Meraki Pain Management Center (Apollo Hospital, Kondapur) provides expert, image-guided care designed to restore your comfort.



Leave a Comment